


Knee: cell therapy applied to osteoarthritis and meniscus and ligament injuries.
The knee bears loads, absorbs impact and needs to stay stable while we walk, run, stand up or play sports. When any of its structures is injured or deteriorates, pain, loss of strength and limitations in moving freely may appear. The damage can occur suddenly after a blow, a fall or a sharp twist, or develop gradually over time. At LYRACELL we evaluate the different structures of the knee to identify the source of the damage and determine whether cell therapy can be part of a personalized treatment.
Personalized cell therapyImage-guidedMinimally invasiveIn-house laboratory
Understanding the knee
The knee is formed by the junction of the femur, the tibia and the patella. Its surfaces are protected by cartilage, while the menisci help cushion and distribute loads and the ligaments help keep the joint stable.
Around it, muscle groups such as the quadriceps and the hamstrings generate and control much of the movement.
That is why knee pain does not necessarily come from a single structure. In many cases, several components may be affected at the same time.
Joint wear and damage
Cartilage can deteriorate progressively, as happens in osteoarthritis. There may also be osteochondral lesions, bone edema and osteophytes that change the joint surface and can cause pain and friction during movement.
Meniscus damage
The menisci play a key role in cushioning and distributing loads inside the knee.
Tears or partial or total removal can reduce that capacity and increase the load on the joint surface, contributing to its deterioration.
Ligament and tendon injuries
The ligaments —such as the cruciate and collateral ligaments— help keep the knee stable.
Sprains or partial or complete tears can alter that stability, increase abnormal loads on the joint and affect the function of the muscles involved in movement.
Tendons can also show inflammation, degeneration or injuries that compromise knee function.

How can it present?
Pain when walking or exercising
Discomfort may appear during movement, when bearing loads or after certain efforts.
Loss of mobility
Fully bending or straightening the knee may become difficult or painful.
Feeling of instability
Ligament involvement can create a feeling of insecurity or lack of control during certain movements.
Loss of strength
Changes in knee mechanics can affect muscle function and contribute to a progressive decrease in strength.
Limits in sports or daily life
Running, climbing stairs, standing up or doing activities that used to feel natural may start to become difficult.
Your own cells, prepared according to the tissues that need treatment.
The knee may show changes at the same time in structures with different biological characteristics. That is why treatment begins by determining which tissues are affected and how extensive the damage is.
The treatment used at LYRACELL combines mesenchymal stem cells obtained from adipose tissue with immune system cells from the blood.
Under the protocols of the Moviglia Method, the LYRACELL team processes the cells in the laboratory and prepares a specific combination according to the type of tissue affected —such as cartilage, bone, ligament or tendon, depending on each diagnosis—.
The stem cells are part of a preparation intended to support biological processes related to tissue repair and remodeling. The immune system cells help direct the preparation toward the structures being treated.
The preparation is applied directly to the structures identified in the diagnosis, with the aim of supporting the functional recovery of the knee.
The combination of both cell types seeks to support the body’s natural repair process, through a personalized approach and under strict medical and safety criteria.

From the laboratory to the knee
The stem cells are obtained from the patient and, together with immune system cells, are processed in the laboratory following the protocols of the Moviglia Method. Based on the diagnosis, the LYRACELL team defines a cell preparation adapted to the structures affected in each case. The application can be performed in the joint space, the bone or the ligament and tendon tissues, depending on the location and characteristics of the damage.


Four stages, one treatment defined by the affected structures.
Not all knee injuries need the same approach. The treatment is defined based on the diagnosis, the extent of the damage and the tissues involved.

1
Evaluation
We review the medical history, any history of trauma and sports activity. Depending on the case, X-rays, ultrasound, MRI or CT are used to assess the condition of the cartilage, menisci, ligaments, tendons and bone.
2
Treatment proposal
The medical team defines the extent of the injury, the structures to be treated, the preparation and the application procedure. If the patient is eligible, adipose tissue and peripheral blood are collected, and a combination adapted to the affected tissues is processed.
3
Application
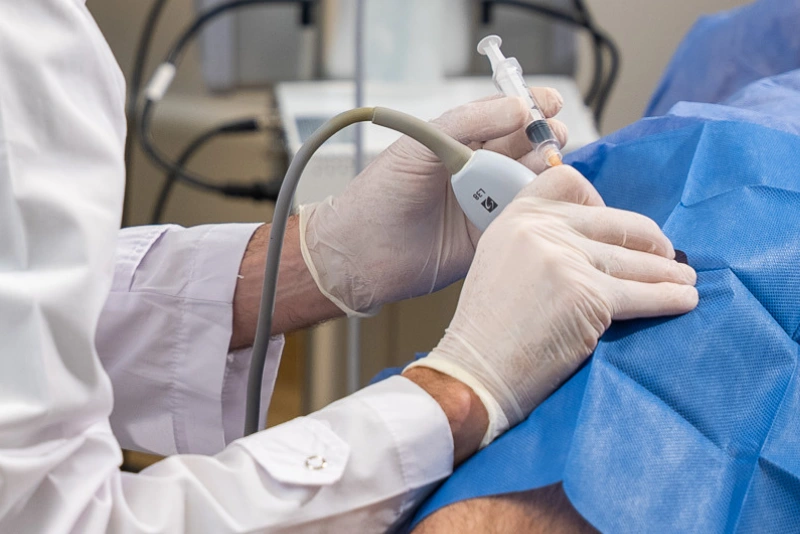
In a minimally invasive way and under image guidance, the preparation is applied into the joint space, the bone or the ligaments and tendons. If surgery is needed to correct the joint surface, reconstruct a ligament or provide stability, the therapy can be added during or after it.

4
Follow-up
At first there may be local discomfort or inflammation. Rehabilitation helps restore range of motion and strengthen the quadriceps and hamstrings. Two or three applications over 6 to 12 months may be considered, with clinical, functional and, if indicated, imaging check-ups.
An accurate evaluation makes it possible to treat the specific problem, not just the pain.
Could this treatment be an option for you?
The indication is defined individually and requires a structural change in the knee that can be confirmed by imaging studies, associated with pain or functional limitation.
It may be an option if…
You have persistent pain or functional limitation in the knee.
There is cartilage damage or degenerative changes that can be confirmed by studies.
You have an injury or deterioration of the menisci that requires a comprehensive evaluation of the joint.
There is involvement of ligaments or tendons that may be suitable for this approach.
You have lost strength, stability or range of motion.
An injury is starting to limit your daily or sports activities.
Several structures are affected and a treatment needs to be defined for each affected tissue.
You want to preserve knee function and act on an identified structural damage.
Another approach may be needed if…
There is very advanced osteoarthritis, with severe loss of joint space or alignment and continuous bone-on-bone contact.
The knee shows extreme instability that requires mechanical repair.
There is a complete ligament tear or another injury that needs surgery to restore the structure or stability of the joint.
The pain originates from a problem in the hip.
The symptoms are related to the involvement of nerve structures coming from the lumbar spine.
Knee studies do not explain the symptoms and another possible cause needs to be investigated.
The indication is defined based on the medical evaluation, the degree of damage and the structures involved.
Images that make it possible to compare progress.
Follow-up images make it possible to compare the condition of the knee before treatment and at later check-ups. They correspond to specific cases: the response, timing and degree of improvement vary from patient to patient.
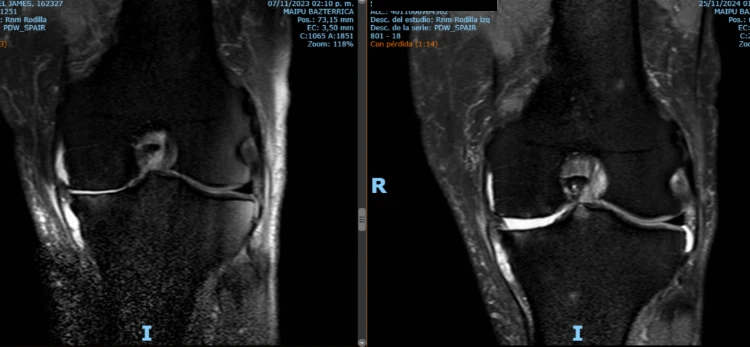
80-year-old patient diagnosed with knee osteoarthritis. Between the two studies (November 2023 and November 2024), the patient received 4 regenerative treatments. Comparing the MRIs, we found:
- More visible and continuous cartilage: the light line covering the bones, where the femur and tibia meet, looks thicker, more defined and more even in the 2024 study.
- Better joint space: the separation between the bones looks more uniform, which indicates better protection of the joint.
- Healthier-looking bone: the area of bone just beneath the cartilage looks more homogeneous and shows fewer signs of irritation.
These results show a visible improvement in the condition of this patient’s joint.
Results may vary from person to person. Each case is evaluated individually.
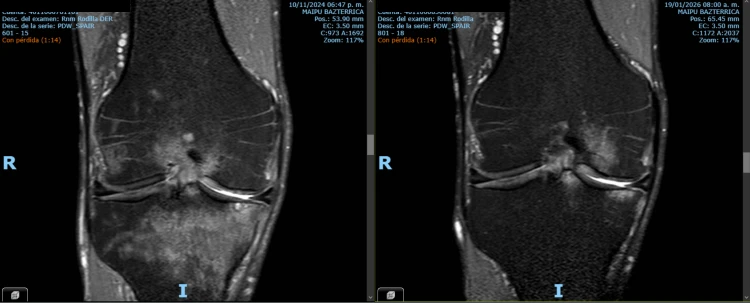
68-year-old patient diagnosed with knee osteoarthritis with bone involvement in the tibia. Between the two studies, the patient received 2 regenerative treatments. Comparing the MRIs, we found:
- Major reduction of edema in the tibia
- Less inflammation in the center of the joint: the light area around the center of the knee is smaller and more clearly defined.
- Healthier bone beneath the cartilage
These results show a visible improvement in the condition of this patient’s bone and joint.
Results may vary from person to person. Each case is evaluated individually.
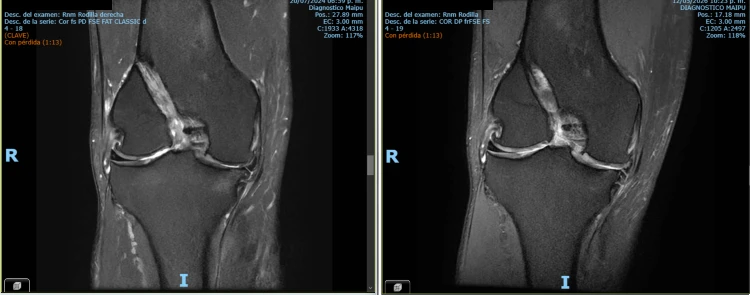
49-year-old patient diagnosed with early osteoarthritis related to sports practice.
Between the two studies (July 2024 and May 2026), the patient received 3 regenerative treatment applications. Comparing the MRIs, we found:
- Less inflammation around the knee: the first study shows light areas in the tissues surrounding the joint, especially on the outer side. In the second study these areas are reduced.
- Preserved cartilage: almost two years later, the line covering the bones remains continuous and shows no signs of further wear.
- Stable joint: the space between the femur and the tibia is maintained, which indicates that the disease did not progress.
These results show that, with the treatment, this patient’s knee remained protected and with less inflammation, despite the demands of sports.
Results may vary from person to person. Each case is evaluated individually.
Treating the tissues is part of the process. So is restoring how they work together.
A knee needs more than structures able to bear loads: it needs mobility, stability and strength working in coordination. That is why, after the application, follow-up is adapted to the treated tissue, the degree of the injury and the activities each patient needs to get back to.
First days
There may be transient local discomfort or inflammation. The medical team provides the corresponding follow-up and defines how to temporarily adapt activities.
Restoring mobility, strength and stability
Physical rehabilitation supports the process of gradually recovering range of motion, strength and movement control.
Work on the quadriceps, hamstrings and other muscle groups helps improve the dynamic stability of the knee and supports a gradual return to activities.
Measurable results
Follow-up makes it possible to assess aspects such as pain, mobility, strength, stability and functional capacity.
When indicated, imaging studies can be repeated to compare the condition of the treated structures with the initial evaluation.
Frequently asked questions
Pain can originate in different structures, such as the cartilage, menisci, ligaments, tendons or bone. In addition, several components may be affected at the same time. That is why diagnosis is the first step in defining the treatment.
The menisci help cushion and distribute loads inside the knee. When they are injured or have been partially removed, this function can be compromised and the load on the joint surface can increase.
No. The indication is defined based on the diagnosis and may be considered for certain damage to the cartilage, bone, ligaments or tendons, as well as for conditions in which several structures are affected together.
Depending on the case, X-rays, ultrasound, MRI or CT may be used to determine which structures are affected and how extensive the damage is.
The base treatment is autologous: the stem cells are obtained from the patient’s own adipose tissue and the immune system cells from their blood. In certain cases, depending on the medical indication, immune system cells from a selected donor may be used.
Depending on the diagnosis, they can be applied into the joint space, the affected bone or the ligament and tendon tissues. The site and the procedure are defined individually.
Depending on the severity of each case, two to three applications spread over a period of 6 to 12 months may be considered. The number is defined at the start of treatment, as part of a plan with specific goals. At the end of the plan, progress is evaluated and, if needed, new interventions are defined.
Some injuries require surgery to mechanically repair a structure or restore the stability of the joint. In those cases, cell therapy can be added during or after the procedure, depending on the medical indication.
Yes. Physical rehabilitation makes it possible to work on mobility, strength and stability. The plan is adapted to the treated tissue, the type of injury and the activities each patient needs to get back to.
Clinical and functional parameters are assessed, such as pain, mobility, strength, stability and the ability to carry out activities. In addition, when indicated, imaging studies can be repeated to compare the condition of the structures with the starting point.
No. Some symptoms may originate in the hip or in nerve structures coming from the lumbar spine. If knee studies do not explain the symptoms, other possible causes need to be investigated.
The first step is understanding which structures are affecting how your knee works.
Every treatment begins with a medical evaluation to determine whether the involvement is in the cartilage, menisci, ligaments, tendons, bone or several structures at the same time, and to define which approach may be right for you.